
Hospital appointment booking in Libya: a pilot plan
A hospital can test Numoo for a specific operational job: organising planned outpatient appointments and giving reception a shared booking record. Start with one suitable clinic, not a whole-hospital rollout. Measure attendance, time spent coordinating and the value of visits actually delivered. Numoo is a booking platform, not an electronic medical record, emergency triage service or hospital information system.
Before you start
- Use one planned outpatient service with clear capacity and a responsible team.
- Keep clinical records and urgent-care decisions in the hospital’s clinical systems.
- Treat financial examples as scenarios; establish your own baseline first.
Choose the part of the hospital that can be scheduled
An outpatient follow-up service with predictable appointment lengths is a more useful starting point than an emergency department. Identify the doctor or resource involved, the days it is available and the number of appointments reception can realistically handle. Allow time for preparation and the work around each visit instead of filling every minute on paper.
Define the boundary in writing. Numoo can organise appointment details and customer contact information; it should not become a place to copy diagnoses, test results or detailed clinical notes. Confirm the hospital’s own access and information-handling requirements before entering patient data. Keep urgent cases on the existing clinical pathway, regardless of what the booking page shows.
One diary needs an agreed reception process
Offer patients the clinic’s booking link for suitable planned visits. Reception can continue helping people who book by telephone or in person, but it must record those appointments in the same operational diary. Otherwise the hospital has added another channel without resolving conflicting promises about availability.
Write a short handover routine: who checks tomorrow’s appointments, who handles a doctor’s absence, who contacts affected patients and who records the final outcome. A cancelled clinic requires a human decision and communication plan; do not assume a booking tool can infer clinical priorities. Test rescheduling and cancellation during training, not during the first busy morning.
What outside evidence can—and cannot—tell you
A 2014 Saudi hospital randomised trial involving 1,499 patients found lower nonattendance with SMS in general medicine (26.3% versus 39.8%) and neurology (29.3% versus 43.9%), but no significant difference in obstetrics/gynaecology. This supports testing reminders; it is not evidence of Numoo’s results or a predicted effect in Libya.
The practical lesson is to measure your own service. Different appointment types, phone accuracy, travel constraints and booking lead times can produce different outcomes. Do not put an external study’s percentage into a sales promise. Record what happened locally, including any groups that still need help accessing appointments.
Turn attendance into a transparent value calculation
Consider an illustrative clinic with 500 eligible appointments in a month. At a 20% no-show rate, 100 appointments are missed. If a measured pilot later records 15% under a comparable definition, the difference is 25 appointments. This is an arithmetic scenario, not a forecast and not a result from a Numoo customer.
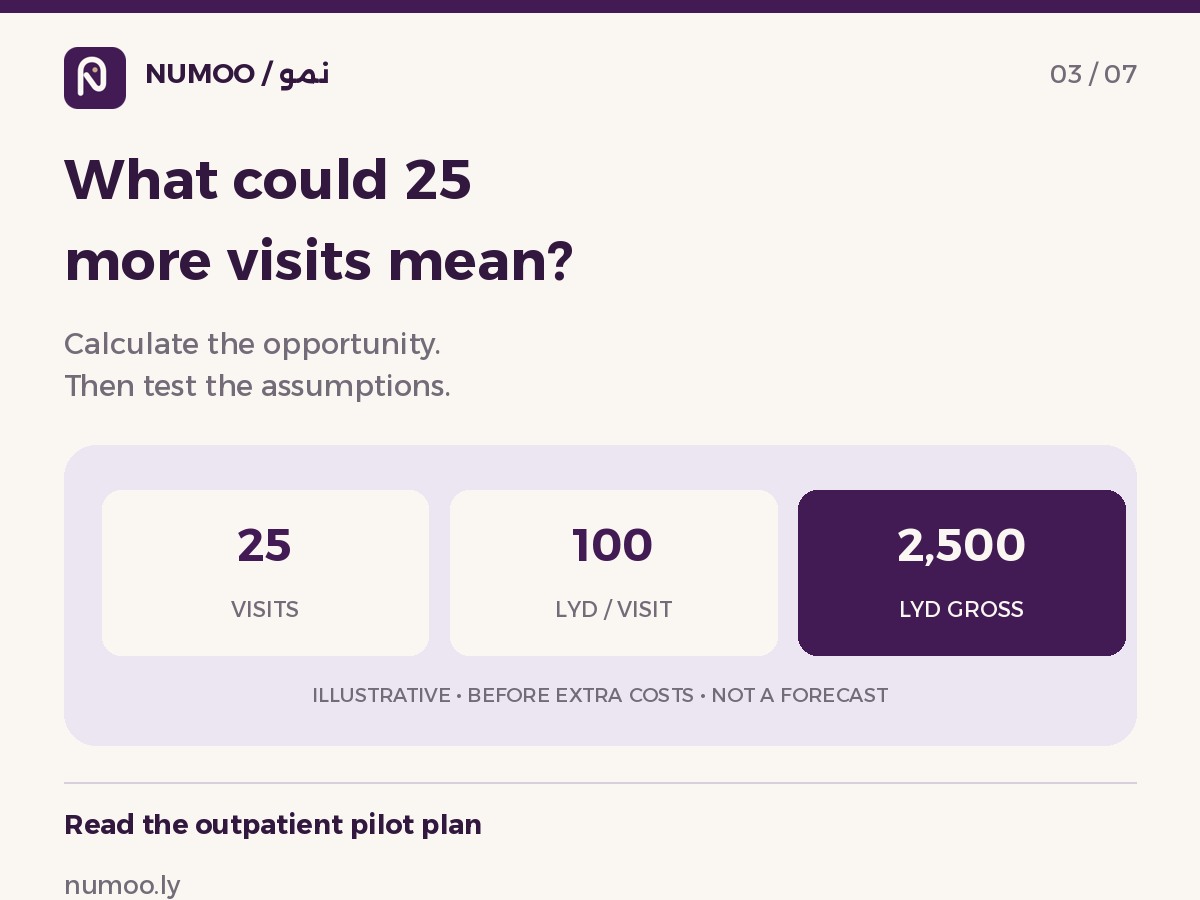
At an assumed 100 LYD collected per additional completed visit, 25 visits represent 2,500 LYD of gross receipts. That is not profit. Subtract incremental clinical costs, communication costs and any additional staffing. Count only visits that actually occurred and were paid; a reservation’s saved value is not payment evidence. If the freed capacity cannot be used, it may provide operational breathing room rather than extra revenue.
| Illustrative input | Value |
|---|---|
| Eligible appointments | 500 |
| Baseline no-shows | 100 / 500 = 20% |
| Pilot no-shows | 75 / 500 = 15% |
| Difference | 25 appointments; 5 percentage points |
| Assumed receipts if all 25 attend and pay 100 LYD | 2,500 LYD before incremental costs |
Measure time saved without inventing a productivity claim
Ask reception to sample how long routine appointment coordination takes before and during the pilot. Separate booking a time from clinical questions: the latter may still need a professional conversation. Include the time spent correcting mistakes and helping patients use the new process, not just the quickest bookings.
For illustration, 200 routine booking conversations shortened by two minutes would release 400 minutes, or six hours and 40 minutes. That does not automatically remove a staffing cost. The useful outcome may be more attention for patients at the desk. Record the actual sample, its dates and its size before describing the result publicly.
A four-week pilot that a hospital can evaluate
Use the first week to check service details, access, phone accuracy and the reception routine. Compare the next weeks with a relevant baseline, keeping clinic type and appointment mix as similar as possible. Record disruptions such as clinician absence, a holiday or a change in opening hours. These can explain a change that would otherwise be wrongly credited to software.
At the review, show appointment counts alongside rates. Include cancellations, completed visits, no-shows, reception time and patient complaints or confusion. Agree whether to continue, adjust or stop the pilot. Expand to another service only when the first team can manage ordinary exceptions reliably.
- Select one service and document its scope and patient-information rules.
- Train reception using demonstration bookings and permitted test numbers.
- Measure attendance outcomes and coordination time with stable definitions.
- Review actual receipts and incremental costs outside the booking-value report.
- Decide the next step from observed results, not a promised percentage.
Common questions
Can Numoo replace a hospital management system?
No. It is a scheduling and booking platform. Clinical records, emergency triage, laboratory systems and medical billing remain outside this workflow. A hospital should assess the proposed appointment use case and its information-handling requirements before a pilot.
How much revenue will a hospital gain?
There is no verified Numoo hospital uplift figure to promise. Potential value depends on additional completed visits, actual collections, available capacity and incremental costs. Use the example as a calculation template and replace every assumption with local observations.
Should a hospital move every department at once?
A narrower pilot is easier to evaluate and support. Start with a planned outpatient service whose appointment lengths and responsibilities are clear. Review patient access, reception workload and outcomes before considering another department.
Put it into practice
This guide describes current product behaviour. Worked examples are illustrative, not customer results or performance guarantees.
Open the illustrated steps in the product guideMake the next step a practical one.
Set up one service and a clear schedule, then start with your business link.
Start your business page